The Science Behind UVThera
UVThera is built on wavelengths, dosing logic, and severity scales that dermatology already trusts — not a new therapy, but a more precise way to deliver an established one.
The wavelengths are the evidence
UVThera devices emit 308nm and 311nm light — the same narrowband ranges used in excimer lasers and NB-UVB units in dermatology clinics worldwide. Decades of published research support their use for vitiligo, psoriasis, eczema, and atopic dermatitis. UVThera's role is to deliver that light with clinic-level accuracy in a smaller, home-usable device.
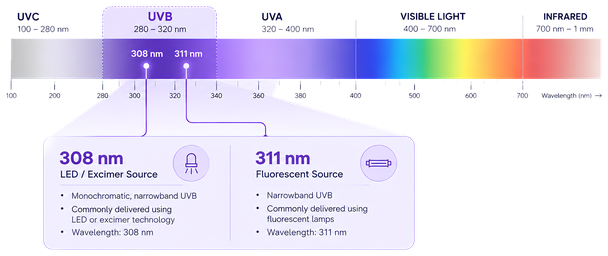
Targeted excimer wavelength, commonly used for localized vitiligo and psoriasis plaques.
Narrowband UVB standard for broader treatment areas in psoriasis and eczema.
A dosing protocol built with a dermatologist, not just an engineer
UVThera's prescribing and dosing protocol was developed in consultation with a dermatology clinical advisor, and follows the same logic clinics already use to keep phototherapy safe and consistent.
- Skin-type-based starting doseInitial exposure set using Fitzpatrick skin typing, not a fixed default.
- Structured escalationDose increases follow defined step-up rules rather than guesswork.
- Built-in hold and step-back logicProtocol accounts for erythema and tolerance, with rules for pausing or reducing dose.
- Condition-specific frequencySession cadence differs by condition, in line with standard phototherapy practice.

Starting dose and escalation pace are set relative to skin type, not applied uniformly.
UVThera's clinical materials — including the prescribing protocol and patient journey — are reviewed by a practicing dermatologist before release.
Measured against the same scales clinics use
Progress on UVThera isn't tracked with a proprietary metric. It's built around the severity indices dermatologists already use to assess these conditions, so what you see on the dashboard maps to what you'd chart in clinic.

Dose you can verify, not just a timer
Most home phototherapy devices rely on a fixed exposure timer, which assumes the LED output never drifts. UVThera devices use real-time photodiode dosimetry — measuring actual light output during a session, not just elapsed time — so the delivered dose stays consistent as the device ages.
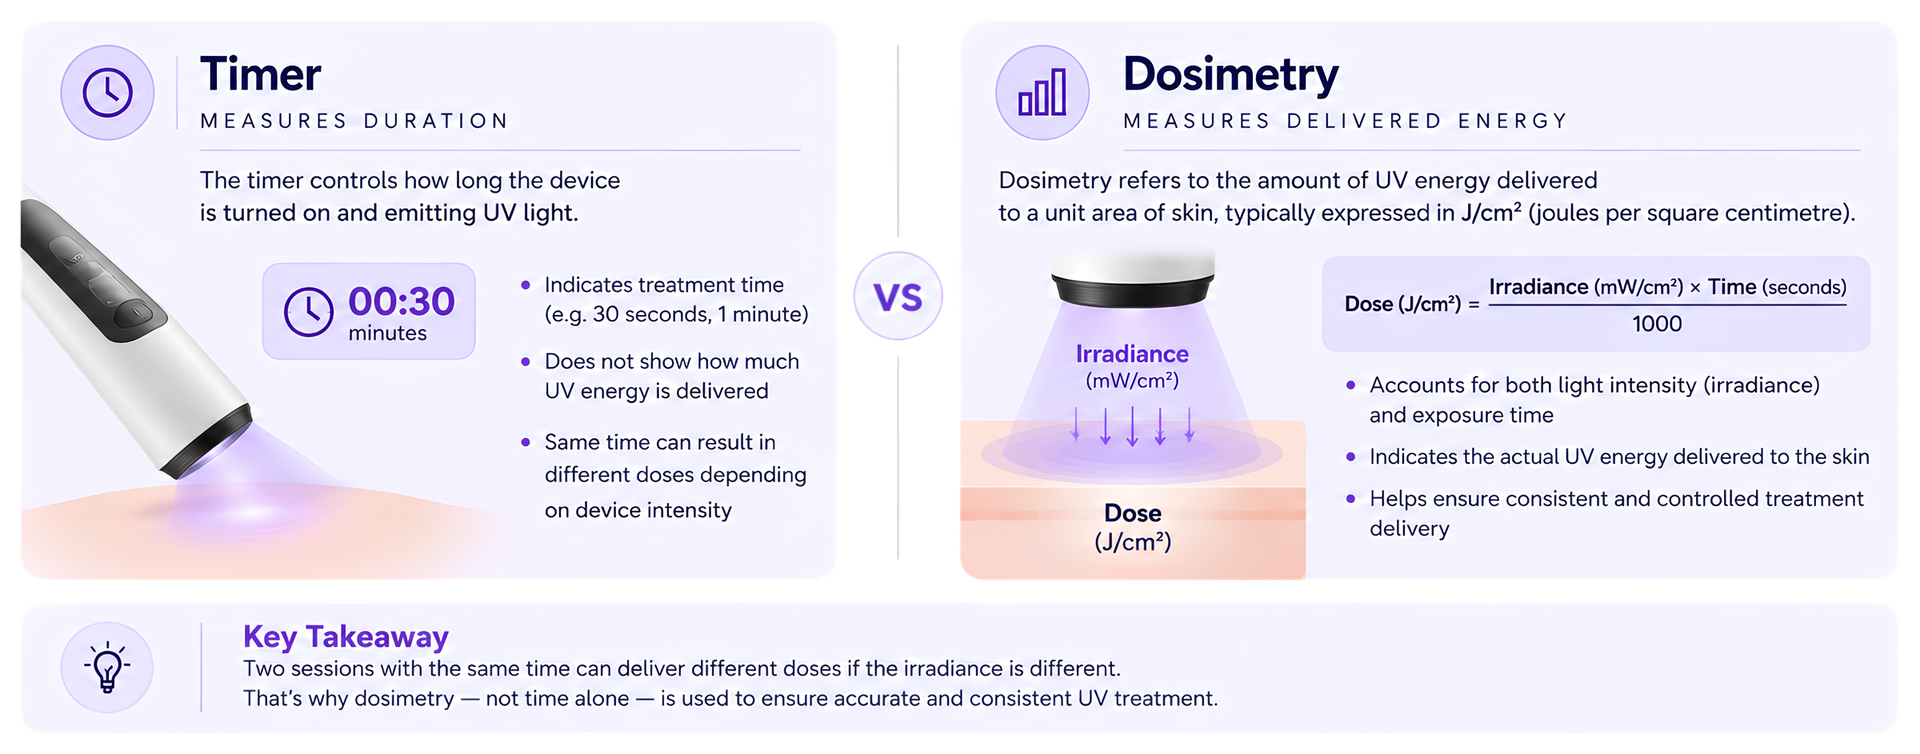
Two sessions with the same timer setting can deliver different doses if the irradiance is different. Dosimetry measures the energy actually delivered to the skin, not just the time the device was on.
UVThera has not yet completed a device-specific clinical trial. The evidence above reflects the published research behind 308nm/311nm phototherapy in general, the clinical protocol UVThera follows, and the engineering behind its dosimetry — not outcome data from UVThera devices specifically. We'll update this page as our own clinical data becomes available.
Selected references
A starting point for your own review — not an exhaustive literature list.
- Elmets CA, Lim HW, Stoff B, Connor C, Cordoro KM, Lebwohl M, et al. Joint American Academy of Dermatology–National Psoriasis Foundation guidelines of care for the management and treatment of psoriasis with phototherapy. J Am Acad Dermatol. 2019;81(3):775–804.
- Gelfand JM, Armstrong AW, Lim HW, et al. Home- vs Office-Based Narrowband UV-B Phototherapy for Patients With Psoriasis: The LITE Randomized Clinical Trial. JAMA Dermatol. 2024;160(12):1320–1328.
- Koek MB, Buskens E, van Weelden H, Steegmans PH, Bruijnzeel-Koomen CA, Sigurdsson V. Home versus outpatient ultraviolet B phototherapy for mild to severe psoriasis: pragmatic multicentre randomised controlled non-inferiority trial (PLUTO study). BMJ. 2009;338:b1542.
- Hauptman M, El Othmani A, Pazhyanur S, Nakamura M. Narrowband-Ultraviolet B Phototherapy for Psoriasis Treatment in Skin of Color: A Systematic Review and Meta-Analysis. Photodermatol Photoimmunol Photomed. 2025.
- Bae JM, Jung HM, Hong BY, et al. Phototherapy for Vitiligo: A Systematic Review and Meta-analysis. JAMA Dermatol. 2017;153(7):666–674.
- Le Duff F, Fontas E, Giacchero D, Sillard L, Lacour JP, Ortonne JP, Passeron T. 308-nm excimer lamp vs. 308-nm excimer laser for treating vitiligo: a randomized study. Br J Dermatol. 2010;163(1):188–192.
- Dayal S, Pathak K, Sahu P, Jain VK. Narrowband UV-B phototherapy in childhood atopic dermatitis: efficacy and safety. An Bras Dermatol. 2017;92(6):801–806.
- Musters AH, Mashayekhi S, Harvey J, Axon E, Lax SJ, Flohr C, et al. Phototherapy for atopic eczema. Cochrane Database Syst Rev. 2021;10:CD013870.
Evaluating UVThera for your practice?
Get dashboard access or talk to our clinical team.
The Science Behind UVThera
UVThera is built on wavelengths, dosing logic, and severity scales that dermatology already trusts — not a new therapy, but a more precise way to deliver an established one.
The wavelengths are the evidence
UVThera devices emit 308nm and 311nm light — the same narrowband ranges used in excimer lasers and NB-UVB units in dermatology clinics worldwide. Decades of published research support their use for vitiligo, psoriasis, eczema, and atopic dermatitis. UVThera's role is to deliver that light with clinic-level accuracy in a smaller, home-usable device.
Targeted excimer wavelength, commonly used for localized vitiligo and psoriasis plaques.
Narrowband UVB standard for broader treatment areas in psoriasis and eczema.
A dosing protocol built with a dermatologist, not just an engineer
UVThera's prescribing and dosing protocol was developed in consultation with a dermatology clinical advisor, and follows the same logic clinics already use to keep phototherapy safe and consistent.
- Skin-type-based starting doseInitial exposure set using Fitzpatrick skin typing, not a fixed default.
- Structured escalationDose increases follow defined step-up rules rather than guesswork.
- Built-in hold and step-back logicProtocol accounts for erythema and tolerance, with rules for pausing or reducing dose.
- Condition-specific frequencySession cadence differs by condition, in line with standard phototherapy practice.
Starting dose and escalation pace are set relative to skin type, not applied uniformly.
UVThera's clinical materials — including the prescribing protocol and patient journey — are reviewed by a practicing dermatologist before release.
Measured against the same scales clinics use
Progress on UVThera isn't tracked with a proprietary metric. It's built around the severity indices dermatologists already use to assess these conditions, so what you see on the dashboard maps to what you'd chart in clinic.
Dose you can verify, not just a timer
Most home phototherapy devices rely on a fixed exposure timer, which assumes the LED output never drifts. UVThera devices use real-time photodiode dosimetry — measuring actual light output during a session, not just elapsed time — so the delivered dose stays consistent as the device ages.
Two sessions with the same timer setting can deliver different doses if the irradiance is different. Dosimetry measures the energy actually delivered to the skin, not just the time the device was on.
UVThera has not yet completed a device-specific clinical trial. The evidence above reflects the published research behind 308nm/311nm phototherapy in general, the clinical protocol UVThera follows, and the engineering behind its dosimetry — not outcome data from UVThera devices specifically. We'll update this page as our own clinical data becomes available.
Selected references
A starting point for your own review — not an exhaustive literature list.
- Elmets CA, Lim HW, Stoff B, Connor C, Cordoro KM, Lebwohl M, et al. Joint American Academy of Dermatology–National Psoriasis Foundation guidelines of care for the management and treatment of psoriasis with phototherapy. J Am Acad Dermatol. 2019;81(3):775–804.
- Gelfand JM, Armstrong AW, Lim HW, et al. Home- vs Office-Based Narrowband UV-B Phototherapy for Patients With Psoriasis: The LITE Randomized Clinical Trial. JAMA Dermatol. 2024;160(12):1320–1328.
- Koek MB, Buskens E, van Weelden H, Steegmans PH, Bruijnzeel-Koomen CA, Sigurdsson V. Home versus outpatient ultraviolet B phototherapy for mild to severe psoriasis: pragmatic multicentre randomised controlled non-inferiority trial (PLUTO study). BMJ. 2009;338:b1542.
- Hauptman M, El Othmani A, Pazhyanur S, Nakamura M. Narrowband-Ultraviolet B Phototherapy for Psoriasis Treatment in Skin of Color: A Systematic Review and Meta-Analysis. Photodermatol Photoimmunol Photomed. 2025.
- Bae JM, Jung HM, Hong BY, et al. Phototherapy for Vitiligo: A Systematic Review and Meta-analysis. JAMA Dermatol. 2017;153(7):666–674.
- Le Duff F, Fontas E, Giacchero D, Sillard L, Lacour JP, Ortonne JP, Passeron T. 308-nm excimer lamp vs. 308-nm excimer laser for treating vitiligo: a randomized study. Br J Dermatol. 2010;163(1):188–192.
- Dayal S, Pathak K, Sahu P, Jain VK. Narrowband UV-B phototherapy in childhood atopic dermatitis: efficacy and safety. An Bras Dermatol. 2017;92(6):801–806.
- Musters AH, Mashayekhi S, Harvey J, Axon E, Lax SJ, Flohr C, et al. Phototherapy for atopic eczema. Cochrane Database Syst Rev. 2021;10:CD013870.
Evaluating UVThera for your practice?
Get dashboard access or talk to our clinical team.